Bloodwork and Diagnostics
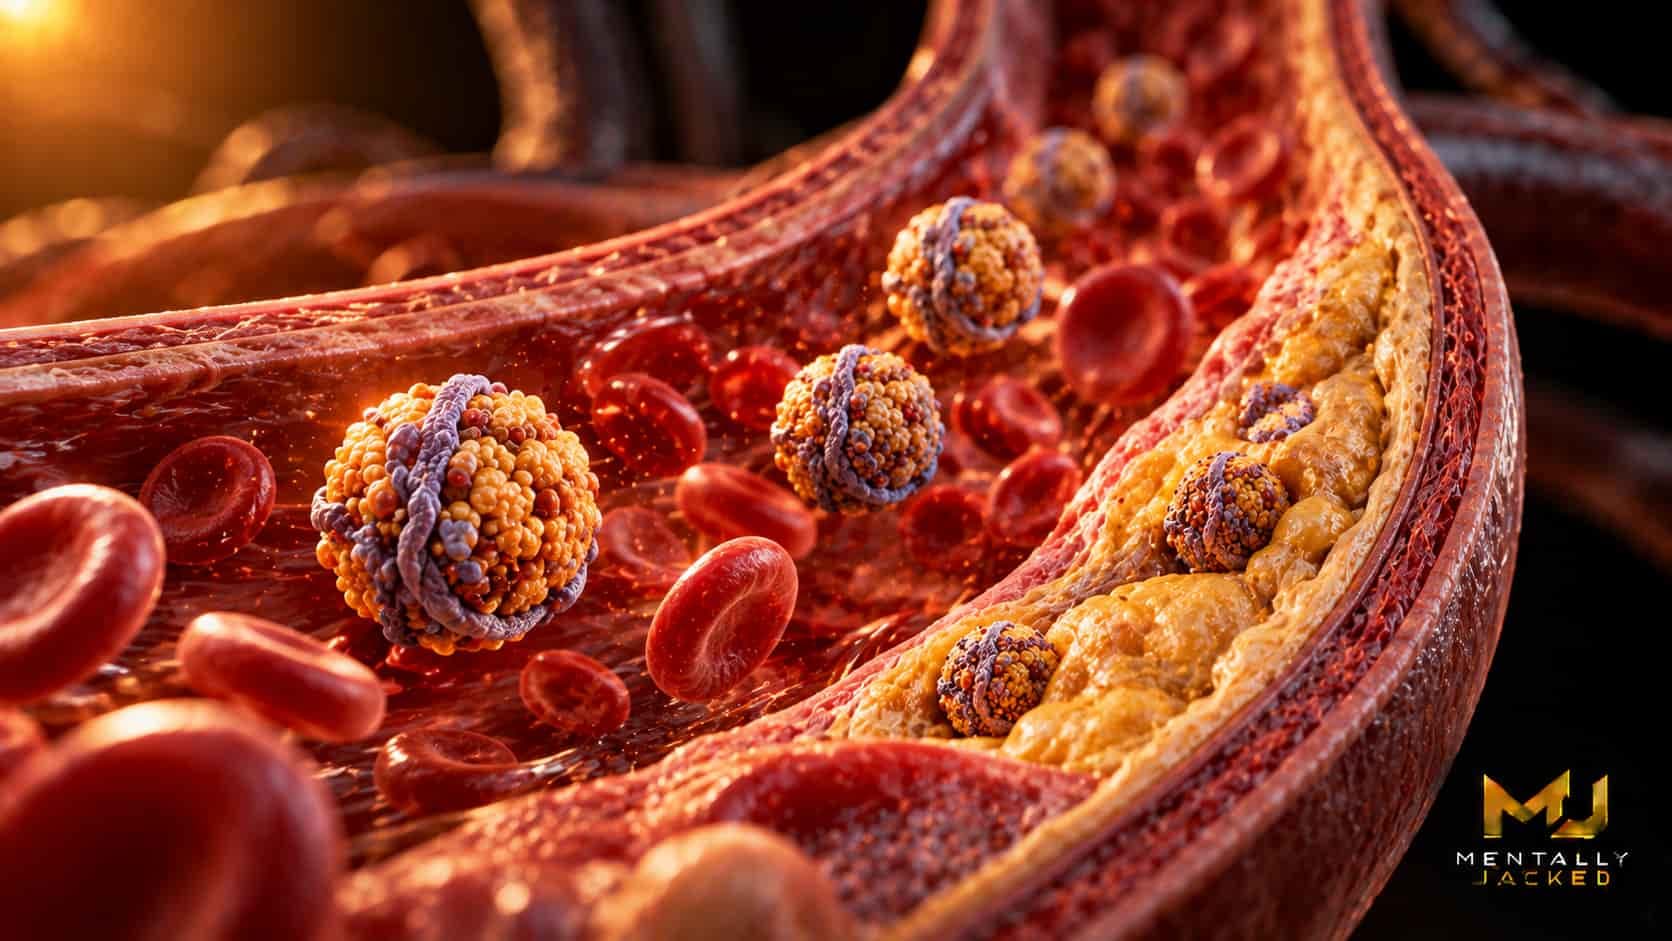
Lipoprotein(a) is the cholesterol particle that a normal lipid panel does not show, that diet and exercise cannot change, and that a fifth of the population carries at a level that roughly doubles their risk of a heart attack.
Most people have never heard of it. Almost nobody in India has been tested for it. On 4 September 2026, the first drug designed to lower it reported its outcome trial. It failed. That result changed what can be said about Lp(a), and here is what it does and does not mean for you.
Lp(a) is an LDL particle with an extra protein, apolipoprotein(a), attached to it. That extra protein makes it more prone to lodge in artery walls, more inflammatory, and more likely to promote clotting than ordinary LDL.
The amount you make is set almost entirely by the LPA gene. It is fixed from early childhood, barely moves with diet, weight or exercise, and stays roughly constant for life. That is why it needs testing only once, and why a high result cannot be trained away.
Around 20 percent of people worldwide have a level high enough to matter. South Asians sit at the higher end of the distribution, and Indian studies have found elevated Lp(a) in a quarter or more of patients presenting with early heart disease.
The evidence that high Lp(a) causes heart disease is about as strong as genetic evidence gets. People who inherit high-Lp(a) gene variants have more heart attacks, more strokes and more aortic valve disease, independently of LDL, blood pressure or anything else.
At levels above 100 mg/dL the risk of a heart attack is roughly doubled, and the risk of aortic stenosis is several times higher.
It also explains a specific type of patient: the lean, active person with normal LDL who has a heart attack at 45. Lp(a) is the first thing to check in anyone with that family history.
Lp(a) is a separate test from the lipid panel and has to be asked for by name. It costs a few thousand rupees at most Indian labs and needs no fasting.
Two units are in use and they are not interchangeable. Roughly, nmol/L is 2 to 2.5 times mg/dL, but the conversion is imprecise and a lab should report one or the other rather than converting. Check which unit your result is in before reading a threshold.
The blood test selector adds Lp(a) whenever the reason for testing includes a family history of early heart disease or a personal history of heart disease with normal LDL, and the cardiac risk score uses it as one of the seven domains it reads.
Pelacarsen, developed by Novartis, is an injected drug that switches off production of apolipoprotein(a) in the liver. It lowers Lp(a) by around 80 percent. The Lp(a)HORIZON trial enrolled more than 8,300 patients with established heart disease and elevated Lp(a), and followed them for years to see whether that reduction prevented cardiovascular death, heart attack, stroke and urgent revascularisation.
On 4 September 2026, Novartis announced that it did not. Lp(a) fell as designed. The events did not.
Two other drugs, olpasiran from Amgen and lepodisiran from Lilly, are in similar trials with results still pending. Whether they succeed where pelacarsen failed is the open question in cardiology this year.
It does not mean Lp(a) is harmless. The genetic evidence that it causes disease was not tested by this trial and remains as strong as it was.
What it suggests is one or more of the following. Lowering Lp(a) late, in people who already have established disease, may be too late to change the course. The damage Lp(a) does may accumulate over decades and not reverse in a few years. Or the amount of reduction needed to change outcomes may be larger than the trial achieved. The genetic studies had already hinted at this: they suggested that a reduction of around 100 mg/dL sustained over a lifetime would be needed to match the benefit of a 1 mmol/L drop in LDL.
For someone reading their own result, the practical conclusion has not changed. A high Lp(a) means everything else that can be controlled needs tighter control, because the one factor that cannot be controlled is working against you.
Nothing lowers Lp(a) meaningfully through lifestyle. Statins can raise it slightly. Niacin lowers it by 20 to 30 percent but has never shown a reduction in events. PCSK9 inhibitors lower it by around 25 percent as a side effect of their LDL action. None of that is the strategy.
The strategy is to lower total risk:
The bloodwork analyzer reads Lp(a) with ApoB, LDL and glucose together, which is where the total picture and the adjusted targets come from.
Anabolic steroids lower Lp(a), often substantially. That sounds like good news and is not. The same compounds raise ApoB, crush HDL, thicken the heart and raise blood pressure, and the net effect on the heart is strongly negative. A cycle is not an Lp(a) treatment.
A high Lp(a) in someone considering a cycle is, if anything, a reason to run cardiac risk more conservatively than usual, because the baseline is already loaded.
Yes. Lp(a) is inherited directly, and a high result in you means each first-degree relative has about a 50 percent chance of carrying it. Parents, siblings and children should each be tested once.
Lp(a) is a genetic cholesterol particle that a normal panel does not show, that lifestyle cannot change, and that raises heart risk independently of everything else. Test it once. In September 2026 the first Lp(a)-lowering drug failed to reduce heart attacks, which leaves the strategy where it was: if it is high, lower LDL, ApoB, blood pressure and glucose harder than you otherwise would, and test your family.
Under 30 mg/dL or under 75 nmol/L is low risk. Above 50 mg/dL or 125 nmol/L is high, and above 100 mg/dL or 250 nmol/L is very high. Check which unit your lab reports before reading a threshold.
No. Lp(a) is set by genetics and barely responds to diet, exercise or weight loss. The strategy for a high result is to lower every other risk factor more aggressively.
Yes. On 4 September 2026 Novartis announced that the Lp(a)HORIZON trial, which enrolled more than 8,300 patients with established heart disease, did not meet its primary endpoint despite lowering Lp(a) substantially. Trials of olpasiran and lepodisiran are still running.
No. The genetic evidence that high Lp(a) causes heart disease is unchanged. The trial suggests that lowering it late, in people with established disease, may not reverse the damage. Prevention through other risk factors still matters.
Once in a lifetime for most people, since the level is genetically set and stable. Retesting is only needed if a result was borderline or if treatment that affects Lp(a) has been started.
Yes. South Asians sit toward the higher end of the Lp(a) distribution, and Indian studies have found elevated levels in a quarter or more of patients with early heart disease.
This article is educational and is not medical advice. See the medical disclaimer.
Want a programme built around your own numbers?
Work With Dinesh
Bloodwork and Diagnostics
Bloodwork and Diagnostics

Bloodwork and Diagnostics
Newsletter
One email when a new guide, calculator or breakdown goes live. Nothing else.
